 how-to
Why Physical Therapy Failed Your Back Pain
Table of Contents
- Why Physical Therapy Fails for Chronic Back Pain
- Signs Physical Therapy Is Not Working
- Chiropractic vs Physical Therapy for Herniated Discs
- Understanding Neurological vs. Musculoskeletal Pain
- Non-Surgical Spinal Decompression for Chronic Back Pain
- How to Advocate for Yourself and Get the Right Diagnosis
- Next Steps: Moving Beyond Failed Physical Therapy
- Frequently Asked Questions
Last Updated: October 4, 2026
Why Physical Therapy Fails for Chronic Back Pain
Physical therapy failed back pain in your case because the root cause was never properly identified.
The problem isn't physical therapy itself. The problem is that PT protocols are designed for acute, mechanical injuries. When your pain stems from something else, degenerative disc disease, nerve compression, central sensitization, or fear-avoidance beliefs, generic exercises won't fix it.
Here's what happens: A therapist evaluates your range of motion, strength, and pain response. They design a program. You follow it faithfully. But nothing changes. The reason is usually one of three things.
Misdiagnosis and Incomplete Assessment
Most physical therapy assessments focus on what they can measure in the clinic: flexibility, muscle strength, movement patterns. What they often miss is the underlying structural problem.
A herniated disc pressing on a nerve requires a different approach than a muscle strain. Degenerative disc disease needs different treatment than a pinched nerve. Yet many PT evaluations don't distinguish between these conditions. They treat the symptoms instead of the cause.
Without imaging, an MRI or CT scan, a therapist is working blind. They might spend months strengthening muscles around a disc that's already collapsed. The exercise doesn't address the actual problem.
The Role of Spinal Pathology in Treatment Failure
Spinal pathology, actual structural damage to discs, vertebrae, or nerve roots, changes everything about treatment. When pathology is present, PT alone often fails because exercises can't reverse the damage.
Consider a herniated disc. The disc material has already bulged out of its normal space and is pressing on a nerve.
Similarly, degenerative disc disease involves the breakdown of disc tissue over time.
This is where many patients hit a treatment plateau. They improve for a few weeks, then stall. Their therapist keeps adding exercises, increasing intensity, trying different techniques.
Psychosocial Factors and Fear-Avoidance Beliefs
Pain isn't purely physical. Your beliefs about your back, and your fear of movement, can actually perpetuate the problem.
Fear-avoidance beliefs (FABQ) are the thoughts that make you avoid movement because you believe it will cause harm (pubmed.ncbi.nlm.nih.gov).
Physical therapists are trained to recognize this, but they can't always overcome it. If a patient believes their spine is fragile and movement is dangerous, they won't fully engage in therapy.
Addressing fear-avoidance requires education, reassurance from imaging results, and sometimes professional mental health support. Standard PT exercises alone won't fix this psychological component.
Signs Physical Therapy Is Not Working
When to Recognize a Treatment Plateau
A treatment plateau looks like this: improvement for 2-4 weeks, then nothing. You feel slightly better initially, but after that, progress stops. You're still doing the exercises, but the pain isn't decreasing anymore.
This typically happens around week 6-8 of therapy. If you're not seeing measurable improvement by this point, less pain, better range of motion, improved function, something isn't working.
Some plateaus are temporary. Your body needs time to adapt. But if you've been in PT for 12 weeks and you're no better than week 6, that's a sign the approach isn't addressing your actual problem.
Red Flags That Warrant a Second Opinion
Several warning signs suggest physical therapy isn't the right treatment for your specific condition.
Your therapist dismisses imaging findings. If an MRI shows a herniated disc or nerve compression and your therapist says "imaging doesn't always correlate with pain" and continues with standard strengthening exercises, get a second opinion.
Pain is getting worse, not better. Mild soreness from new exercises is normal. Increasing pain is not.
You're being treated identically to other patients. Good PT is personalized. If your therapist gives the same exercises to everyone with "back pain," they're not addressing your specific condition.
Your therapist has never mentioned imaging, spinal pathology, or structural problems. They focus only on muscles and movement.
Chiropractic vs Physical Therapy for Herniated Discs
How Spinal Manipulation Differs From PT Exercises
Chiropractic care emphasizes spinal manipulation, manual adjustments intended to restore alignment and reduce nerve pressure. Physical therapy emphasizes exercise, stretching, and movement patterns to build strength and improve function.
These are fundamentally different approaches. Manipulation is passive (the provider does it to you). Exercise is active (you do the work). For a herniated disc, the distinction matters.
Spinal manipulation can provide temporary pain relief by reducing muscle tension and improving joint mobility. Many patients feel better immediately after an adjustment.
Physical therapy builds muscular support around the spine, which can help stabilize a herniated disc and reduce symptoms over time.
Evidence and Limitations of Each Approach
Both chiropractic care and physical therapy have research support for pain relief in certain situations. Spinal manipulation shows modest short-term benefits for acute low back pain (pubmed.ncbi.nlm.nih.gov).
CALL TODAY TO SCHEDULE YOUR FREE CONSULTATION →
Neither approach is effective for structural problems like significant disc herniation or advanced degenerative disc disease. Both reach their limits when the problem is mechanical pressure on a nerve, something that requires decompression, not just manipulation or exercise.
This is crucial: if you have a herniated disc compressing a nerve, chiropractic adjustments and PT exercises address the symptoms, not the source. Neither will decompress the nerve or reduce the pressure.
Understanding Neurological vs. Musculoskeletal Pain
Your pain might feel the same, but its origin determines what will actually help.
Musculoskeletal pain comes from muscles, tendons, ligaments, or joints. It's usually worse with specific movements, improves with rest, and responds well to strengthening and stretching.
Neurological pain comes from nerve compression or irritation. It often radiates down the leg (sciatica), causes numbness or tingling, and doesn't improve predictably with exercise.
The difference is critical.
A proper assessment should determine which type of pain you have. This typically requires imaging and neurological testing (checking reflexes, sensation, muscle strength).
Non-Surgical Spinal Decompression for Chronic Back Pain
How Decompression Targets Disc and Nerve Pressure
Spinal decompression is a non-surgical treatment designed to reduce pressure on discs and nerves.
The treatment is passive, you lie on a specialized table while the machine applies controlled, graduated traction. This creates space between vertebrae, reducing the pressure that's been causing your pain and neurological symptoms.
Decompression is particularly effective for herniated discs, pinched nerves, and sciatica caused by disc pathology. It targets the actual source of the problem: the pressure on the nerve.
When Decompression May Be the Right Next Step
If you've completed 8-12 weeks of physical therapy without improvement, and imaging shows a herniated disc or nerve compression, decompression is worth considering.
Decompression is also a good option if you want to avoid surgery but conservative care hasn't worked.
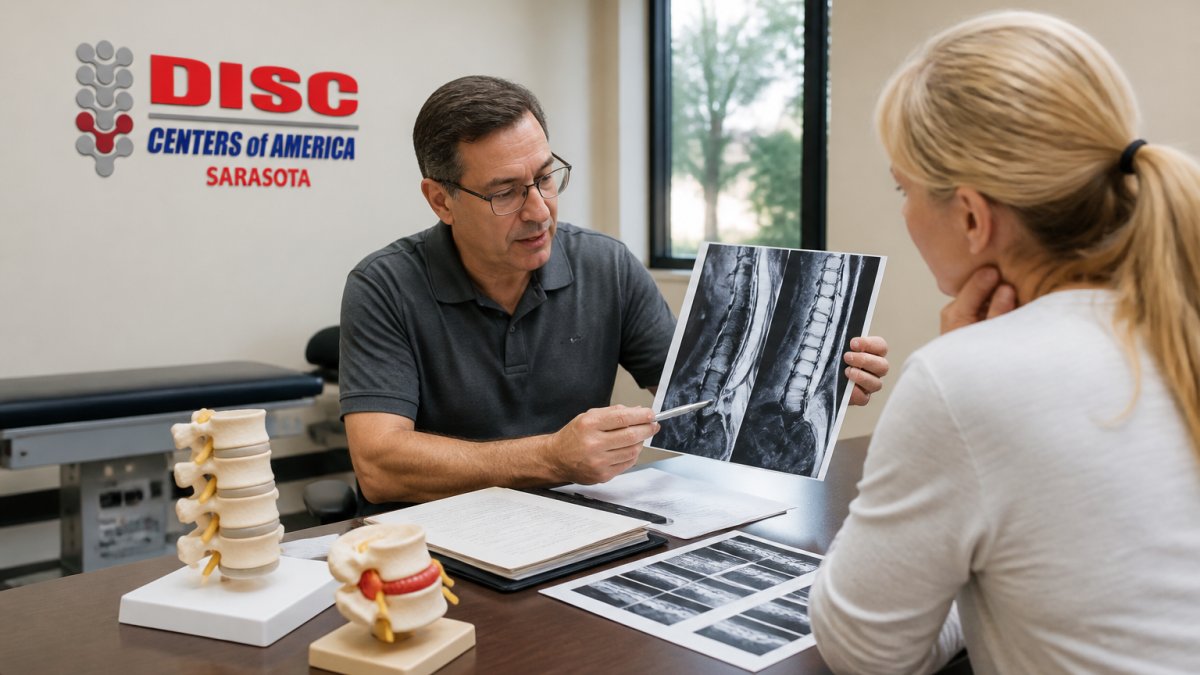
At Sarasota Disc Center, we've helped patients with physical therapy failed back pain find relief through spinal decompression.
How to Advocate for Yourself and Get the Right Diagnosis
Questions to Ask Before Starting or Continuing Treatment
Before beginning any treatment, or before continuing one that isn't working, ask these questions:
- Has imaging (MRI or CT) been done? If not, why not?
- What does the imaging show? Are there disc problems, nerve compression, or other structural issues?
- How does this treatment address my specific diagnosis?
- What should I expect to see improve in the first 4-6 weeks?
- If I'm not better by week 8, what's the next step?
- Is this treatment designed to fix the problem, or just manage the pain?
These questions force clarity. A good provider will answer them directly. A provider who gets defensive or dismissive is signaling that they don't have a clear plan for your specific condition.
When and How to Seek a Second Opinion
Seek a second opinion if:
- You've been in treatment for 12 weeks with no measurable improvement
- Your pain is worsening despite treatment
- Your provider can't explain why treatment isn't working
- You have imaging findings that don't match your treatment plan
- You're considering surgery and want to explore conservative options first
When seeking a second opinion, bring your imaging (MRI, CT scans) and a clear description of your symptoms, what makes them worse, and what treatments you've tried. A new provider needs this context to give you an informed evaluation.
A second opinion isn't disloyal. It's smart. Your health is too important to continue with a treatment that isn't working just because you've already invested time in it.
Next Steps: Moving Beyond Failed Physical Therapy
Physical therapy failed because it didn't address your actual problem. That's not a failure of PT as a treatment, it's a failure of diagnosis and treatment selection.
The path forward requires three things: accurate diagnosis through imaging, understanding whether your pain is structural or functional, and choosing treatment that matches your actual condition.
If you have a herniated disc, degenerative disc disease, or nerve compression causing your pain, non-surgical spinal decompression offers a different approach.
At Sarasota Disc Center, we start with a thorough evaluation and imaging review. We identify exactly what's causing your pain.
| Treatment Type | Best For | Limitations |
|---|---|---|
| Physical Therapy | Muscle weakness, movement dysfunction, acute injuries | Doesn't address disc herniation or nerve compression |
| Chiropractic Manipulation | Temporary pain relief, joint mobility | Doesn't reduce disc herniation or decompress nerves |
| Spinal Decompression | Herniated discs, nerve compression, sciatica | Requires accurate diagnosis and proper candidate selection |
| Surgery | Severe pathology unresponsive to conservative care | Invasive, recovery time, potential complications |
Frequently Asked Questions
Why did my physical therapy for back pain fail when the therapist said it was the right treatment?
Physical therapy fails when the underlying spinal pathology, such as a herniated disc, degenerative disc disease, or nerve impingement, isn't properly diagnosed or when the condition requires a different treatment approach. PT is effective for some types of back pain, but if your pain stems from disc pressure on a nerve or central sensitization, exercise alone may not resolve it. A thorough diagnostic assessment, including imaging, can clarify whether your condition needs a different intervention.
How is non-surgical spinal decompression for chronic back pain different from physical therapy?
Non-surgical spinal decompression uses mechanical traction to reduce pressure on discs and nerves, directly addressing the source of pain. Physical therapy focuses on strengthening muscles and improving mobility through exercise. If your disc is herniated or pressing on a nerve, decompression targets that pressure directly, while PT alone may not reduce it. Many patients find relief with decompression when PT has plateaued, especially for nerve-related pain.
What is the difference between chiropractic care and physical therapy for a herniated disc?
Chiropractic care typically uses spinal manipulation (adjustments) to improve alignment and mobility, while physical therapy uses targeted exercises and manual techniques to strengthen supporting muscles. For herniated discs, chiropractic adjustments may provide temporary relief but don't reduce disc pressure the way spinal decompression does. PT strengthens muscles but may not address nerve compression. Each approach has limitations; the best option depends on your specific diagnosis and whether nerve pressure is the primary issue.
After failed physical therapy, how do I know if I should try a different treatment or see another doctor?
If you've completed 6-8 weeks of consistent physical therapy with no improvement in pain or function, it's time to seek a second opinion. Red flags include worsening symptoms, new numbness or weakness, or pain that limits daily activities. Ask your current provider whether imaging (MRI or CT) has ruled out serious pathology. A second opinion from a specialist trained in diagnostic imaging and non-surgical options can clarify whether your condition requires a different approach, such as spinal decompression or injections.
If physical therapy didn't work, the reason is usually clear once you have the right diagnosis. Spinal decompression at Sarasota Disc Center addresses what PT couldn't: the actual mechanical pressure on your disc and nerve. Dr. David Cifra and our team use advanced, non-invasive technology to target the source of your pain. Call for a free MRI review and consultation to find out if decompression is right for you.